


The mental health decline of our Nation’s children and young adults is beyond the crisis point, and the #1 cause of it is Childhood Developmental Trauma. The Seacoast of both New Hampshire and Maine suffered another tragic youth suicide in May 2025 when 16-year-old Jonathan “Jony” Hunter jumped from the high Piscataqua River Bridge which connects the two states across a deadly current. Unfortunately, the narrative after most publicized suicides gets side tracked by community mental health agencies and 501c(3) organizations like NAMI chapters with empty calls for “suicide prevention”. However, I believe, as a mental health counselor who has worked on the front lines for decades with suicidal children and youths, suicide prevention is too late—We need childhood trauma prevention. As the mother of Brycen Robert Rylan Couture, my beloved 23-year-old son who ended his physical life on September 27, 2017, I will reiterate and repeat this louder still: SUICIDE PREVENTION IS TOO LATE—WE NEED CHILDHOOD TRAUMA PREVENTION!

I am uncompromising on this position because suicide isn’t “a cause” of itself, nor is “mental illness” the root. Suicide and mental illness are the weeds that grow from the already wounded root; they are tragic symptoms of a much greater problem—a problem that often has a multitude of holistic stressors feeding into it dating back to early childhood distress. To understand this, let’s take a look at the wounded root of a close relative of suicide, addiction.
Research by Gabor Maté and the Adverse Childhood Experiences (ACEs) Studies indicates that chemical and behavioral addictions are the brain’s way of attempting to restore a healthy brain chemistry that was disrupted by early childhood distress. Daniel Sumrok, director of the Center for Addiction Sciences at the University of Tennessee Health Science Center refers to addiction as “ritualized compulsive comfort-seeking”. He explains that “Ritualized compulsive comfort-seeking (what traditionalists call addiction) is a normal response to the adversity experienced in childhood, just like bleeding is a normal response to being stabbed” (Stevens, J. E., 2017, May 2). In other words, addiction isn’t “the cause” of “ritualized compulsive comfort-seeking”, childhood distress is. Likewise, “mental illness” isn’t “the cause” of suicide—the childhood distress compromising the victim’s ability to cope with the current stressor is the cause. Like bleeding is a normal response to being stabbed, suicide has been a reaction throughout the history of humanity to being “emotionally stabbed” to the point of it being unendurable.
The “mental illness” model of suicide prevention is decades outdated just like the behavioral-biochemical model of treating mental illness, especially in children, is about a century outdated. These models persist for a few reasons:
These models generate millions annually in profits, donations, and funding to community mental health centers (which accept Medicaid) and 501(c)(3) organizations like NAMI and CHADD.
These models suggest that “mental illness” is primarily organic and genetic rather than the symptom patterns of how individuals or members of a family express the pain of childhood distress, loss, and trauma.
These models suggest that suicide is often due to a “mental illness” or immediate circumstance rather than a symptom of how an individual reacted to the anguish of current circumstances that triggered their childhood distress, loss, and trauma.
Current research supports a childhood developmental trauma model of both mental health suffering and suicide. This isn’t about blaming anyone—Childhood trauma is often generational and society-induced. This model supports a neuro-somatic (brain-body) and attachment (parent-child relationship) approach to understanding and healing childhood distress, grief, and trauma. Trauma, especially pre-verbal trauma in the first three years of life, gets “stuck” in the limbic system of the brain, specifically enlarging and “wounding” the amygdala, our brain’s “panic button”. The amygdala triggers us to fight-flight-or-freeze when we are in danger—or when we perceive danger from a trauma trigger. This is even more salient for youths, whose pre-frontal cortexes do not complete development until age 26, meaning that they can’t easily over-ride impulsive actions with future-focused reasoning. For a traumatized youth, suicide is certainly within the scope of a fight-flight-or-freeze reaction to a trauma threat cue.
A neuro-somatic and attachment approach to healing trauma and preventing suicide may include:
EMDR
Neurofeedback
EMDR with Somatic Experiencing
Attachment-Focused Family Therapy
Referrals for adjunct supports and therapies
Alternative education or homeschooling
OT/PT
Functional nutrition support
Functional medicine or osteopathy
You can learn more in my book, Nurturing and Empowering Our Sons. Over years of working with children, youths, and families, I developed a treatment protocol, The Couture Protocol (TCPC) that uses a 12-dimensional system of healing Childhood Developmental Trauma. TCPC includes all of the above.

When my son was involved in these services and supports, he was stable, happy, and thriving.

Why do NAMI and community mental health centers primarily push the “mental illness” model of suicide prevention? They would lose their millions in funding if they pivoted to a primarily childhood developmental trauma model. While “mental illness” is presented in the behavioral-biochemical model as being as elusive and contagious as catching the flu, childhood developmental trauma and its “parent trauma”, generational trauma, are preventable scourges that can be healed and ended. This, of course, means that the push for pharmaceuticals and talk therapy would also reduce and possibly end. NAMI’s model focuses on reducing the “stigma” of mental illness because this work—and the funds receivable—never ends. But, there is currently no stigma to mental illness in today’s world. Therapy has been in vogue since the late ‘80s and amongst some Gen Z youths, mental illness is viewed as a badge of coolness. Perhaps NAMI has overdone it!
To be clear, pharmaceuticals and talk therapy, including Cognitive Behavioral Therapy models, do not heal trauma, and tend to make childhood developmental trauma worse. The neuro-somatic and attachment treatments that do heal traumas tend to be brief and multi-modal rather than drag on non-stop for many years— sometimes for most of a child’s childhood—as in the case of talk therapy and psychiatric drugging. Neuro-somatic and multi-modal trauma therapies support the private practitioners who pour their hearts into helping individual children and families heal, while the behavioral-biochemical model funds community mental health clinics that function like factories, pumping labels and drugs into children, separating parents from the treatment room, and burning out the light and energy of clinicians via shockingly high caseloads and productivity requirements.
What is the harm to the public of NAMI and community mental health centers pushing the “mental illness” model of suicide prevention? First, this approach might be well-meaning, but it is misleading and inaccurate. Lives that could be saved by a trauma-focused, attachment-focused approach and a change in educational environment are lost to pushing youths through years of trauma-triggering talk therapy, cocktails of psychiatric drugs, IEPs and 504 plans, socio-political propaganda, and separating parents from the treatment room, all while ignoring the childhood trauma, generational trauma, attachment, educational, nutritional, neuro-developmental, sensory, social, and even socio-political distress that underlies suicidal ideation.
Let’s touch on one of the greatest socio-political distress points facing youths today—and it won’t be what you are expecting: Boys and young men have been vilified in schools, in the media, and in socio-political discourse since the late 1990s. With children growing up in the public school system hearing that “girls rule, boys drool”, that masculinity is “toxic”, and that males are responsible for the problems of the world, our male youths have been growing up with an increasing sense of worthlessness, shame, rejection, and self-hatred. Moreover, sexual assault of boys and young men is minimized and overlooked, especially when the perpetrators are female. According to CDC data, males are also the cohort most vulnerable to suicide: Nearly 80% of all suicide victims of all ages are male and, regarding youths, 81% of youth suicide victims ages 10-24 are boys and young men. Yet, NAMI has not sounded the alarm that suicide is an epidemic of males. (Learn more about the plight of our sons in my book, Nurturing and Empowering Our Sons).
So, what childhood trauma prevention efforts DO help prevent suicide?
First, The National Suicide Prevention Lifeline crisis and suicide lifeline is a literal lifesaver for immediate crisis situations: Call or text 988 from anywhere in the United States for 24-7 help.
If you have any suspicion that your child is feeling suicidal, use the Columbia Suicide Severity Rating Scale (C-SSRS) for Parents and call 911 or 988 if risk is imminent: https://cssrs.columbia.edu/the-columbia-scale-c-ssrs/cssrs-for-communities-and-healthcare/#filter=.general-use.english
If your child is acting-out at school, or depressed, bored, anxious, or hyperactive at school, take this seriously! These symptoms are natural alarms signaling that something in that environment is distressing your child. Bullying is another issue to take very seriously. I recommend alternative educational options, such as learning pods, homeschooling, micro school, child-centered private school, charter school, outdoor nature school, arts-based school, or independent study program.
If your child is depressed, anxious, angry, agitated, withdrawn, hyperactive, having meltdowns and outbursts, showing aggression, or any change in functioning, seek EMDR therapy with attachment-focused family therapy.
If your child has a known history of abuse, neglect, loss, being bullied, foster care, adoption, or other trauma, seek out neuro-somatic trauma treatments such as EMDR, Neurofeedback, or Somatic Experiencing, as well as attachment-focused family therapy. Individual therapy is not developmentally appropriate for most children 18 and under.
Work with a functional medicine doctor or osteopath for a nutritional, gut microbiome healing approach to emotional healing as well as for an alternative to psychiatric drugs.
A child with any mental health symptoms that are not resolving should have a full medical work up to rule out any medical issues.
If your child has sensory sensitivities that lead to emotional dysregulation, or if your child has a neurodevelopmental disability, work with an occupational therapist (OT) with a sensory processing specialty.
NEVER attempt to taper your child off of psychiatric drugs without the support of a doctor or holistic healthcare specialist and NEVER have your child stop psychiatric drugs cold turkey— This is very dangerous!
Get your children out in nature and off screens—Research supports that screen use leads to depression, anxiety, and mental health decline in children and youths, while nature has the opposite—a healing, rejuvenating, calming effect on kids.
Do not expose your child to socio-political media or materials that shame boys and men, nor that frame sexual assault as a gender issue—Like physical assault, sexual assault is a human crime, not a gender crime.
A truly happy, healthy child or youth does not just suddenly end his life. Often, suicide is a dark, recurring pull that a youth fights over time or it occurs in a flash following a major psychological blow to the heart. However, the root wound in both cases is almost always something deeper and more complex: It may involve a neurological or nutritional issue, unmet emotional or physical needs, distressing school environment, screen use (especially social media, video games, TikTok, and AI chatbots), early childhood separation from parents (daycare, school, loss, foster care), early childhood medical distress (circumcision, injury, emergency, procedure, surgery), loss or death of a loved one, or suffering or witnessing bullying, family violence, child sexual abuse, child neglect, media violence, community violence, war, or other trauma.
My son, Brycen, who I adopted at age 11, felt the dark pull of suicide starting at age five when he made a very real suicide attempt at a “therapeutic” preschool. “Suicide prevention” efforts wouldn’t have prevented the misery that provoked that five-year-old child’s act; the misery of enduring two sexual assaults, physical and emotional abuse and neglect, loss of his birthfamily, of living in multiple foster placements—including a group home, and the frustration of schools that punished his behavior rather than focused on his brilliance.
By the time my son’s dream of a forever family to call his own came true at age 11, he had moved through a total of 15 different foster, respite, and residential (group) placements and suffered additional abuse and neglect, losses, rejections, and traumas. As he was turning 11 near the cusp of Christmas, Brycen wished upon a star, prayed to God, and asked Santa Claus for a forever family—but with a harrowing challenge: If he didn’t receive a family by the end of January (he told me he “gave God, Santa, and the star a one month grace period”), he would end his life. I have no doubt in my mind that he would have done so, given how literal and hyperfocused he was.
Thank God, Santa, and Star that he learned in the nick of time that he would be meeting his forever family soon. However, had we not met the day we did in January, “suicide prevention” efforts wouldn’t have prevented the misery Brycen felt while languishing in the foster care system without a family to call his own. Take a look at the photos of my son below and it is clear that only the power of love was able to heal that misery (See captions below the photos).


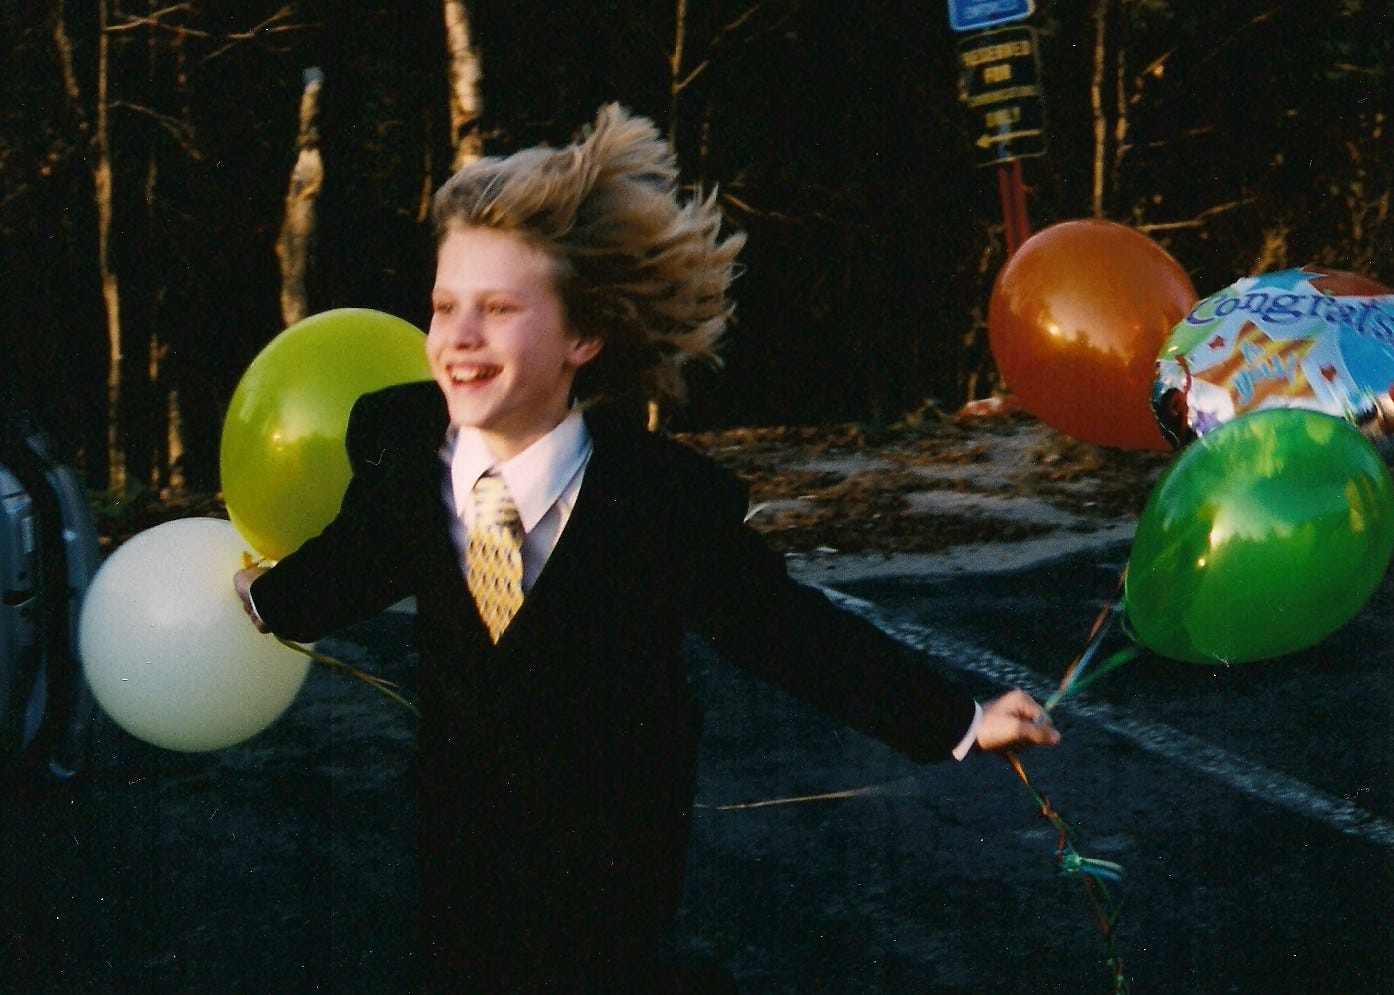
Brycen lived fully, passionately, deliberately, and with unceasing creative, industrious brilliance in our almost-13 years together. He learned what true joy and safety felt like; what it meant to be loved unconditionally, cherished, wanted, nurtured, showered with love, and supported in all his endeavors. Through homeschooling, Brycen was able to bring dreams to fruition, especially of being a performing singer and songwriter, and enjoy the daily support of family, friends, and community for all of his active adventures, inventions, creative talents, communing with nature, and his spiritual musings.


Brycen was a loving, peaceful, deeply empathic soul who took the healing opportunities he was given and became the kind of young person who would be rare in today’s divided, aggressive, dehumanizing world: Through his writing, music, public speaking, and his actions, Brycen called for love for all of humanity, especially for showing unconditional love to children, as the way to peace. Of course, “Suicide prevention” efforts didn’t create that for Brycen; an unconditionally committed, tirelessly engaged, and unconditionally loving family did.
“Suicide prevention” efforts did not prevent the spiral of forces working against his emotional stability at ages 22 and 23 that threw Brycen off course and away from his support system. During this time, he suffered a severe relapse of Post Traumatic Stress Disorder that included dissociative episodes with breaks from reality. This was amplified by him being on the autism spectrum with sensory processing challenges, having medical and food allergy challenges, and coming off of his Paleolithic diet that had helped reduce inflammation in the brain and gut—Inflammation in the gut and brain is believed to exacerbate mental health symptoms. He became an expectant father in a distressing situation. When he believed that his future hopes for his unborn daughter were shattered, his early childhood loss, rejection, and trauma were triggered. These echoes reared up like the beasts in his Dungeons & Dragons campaigns and overwhelmed him. “Suicide prevention” efforts couldn’t have fixed it.
Brycen’s suicide has devastated me, our family, his birthfamily, his friends, and all who love him. His suicide, and all of the additional losses that have come with losing him, will likely leave a mark of grief on my beloved granddaughter someday. In spite of this devastation, I realize that Brycen living out almost 24 years was a miracle. According to the ACEs studies, a person with an ACE score of 6 is nearly 3000% more likely (2,790%) to attempt suicide than a person with an ACE score of 0! Brycen would have near-maxed out the 10 ACEs included in the studies, and he had multiple traumas that the ACEs studies did not include. Brycen, like most youth suicide victims, did the best he could to stay alive as long as he did.
With what we know about ACEs, or better yet, childhood trauma, humans are amazingly resilient… but only to a point. Trauma passes on through the DNA, rewires our brains, and permanently alters our sense of safety and the trajectory of our lives. Our vulnerable children and youths need nurturing support and multi-holistic healing on every developmental level as true prevention of suicide. Immediate suicide crisis interventions like 988 and the C-SSRS are important for in-the-moment lifesaving. Beyond that, “suicide prevention” campaigns are too little, too late because they ignore childhood trauma and treat “mental illness” like a bee sting that one suddenly gets. We need childhood developmental trauma prevention now and going forward—The lives of our Nation’s young people are at stake!
